
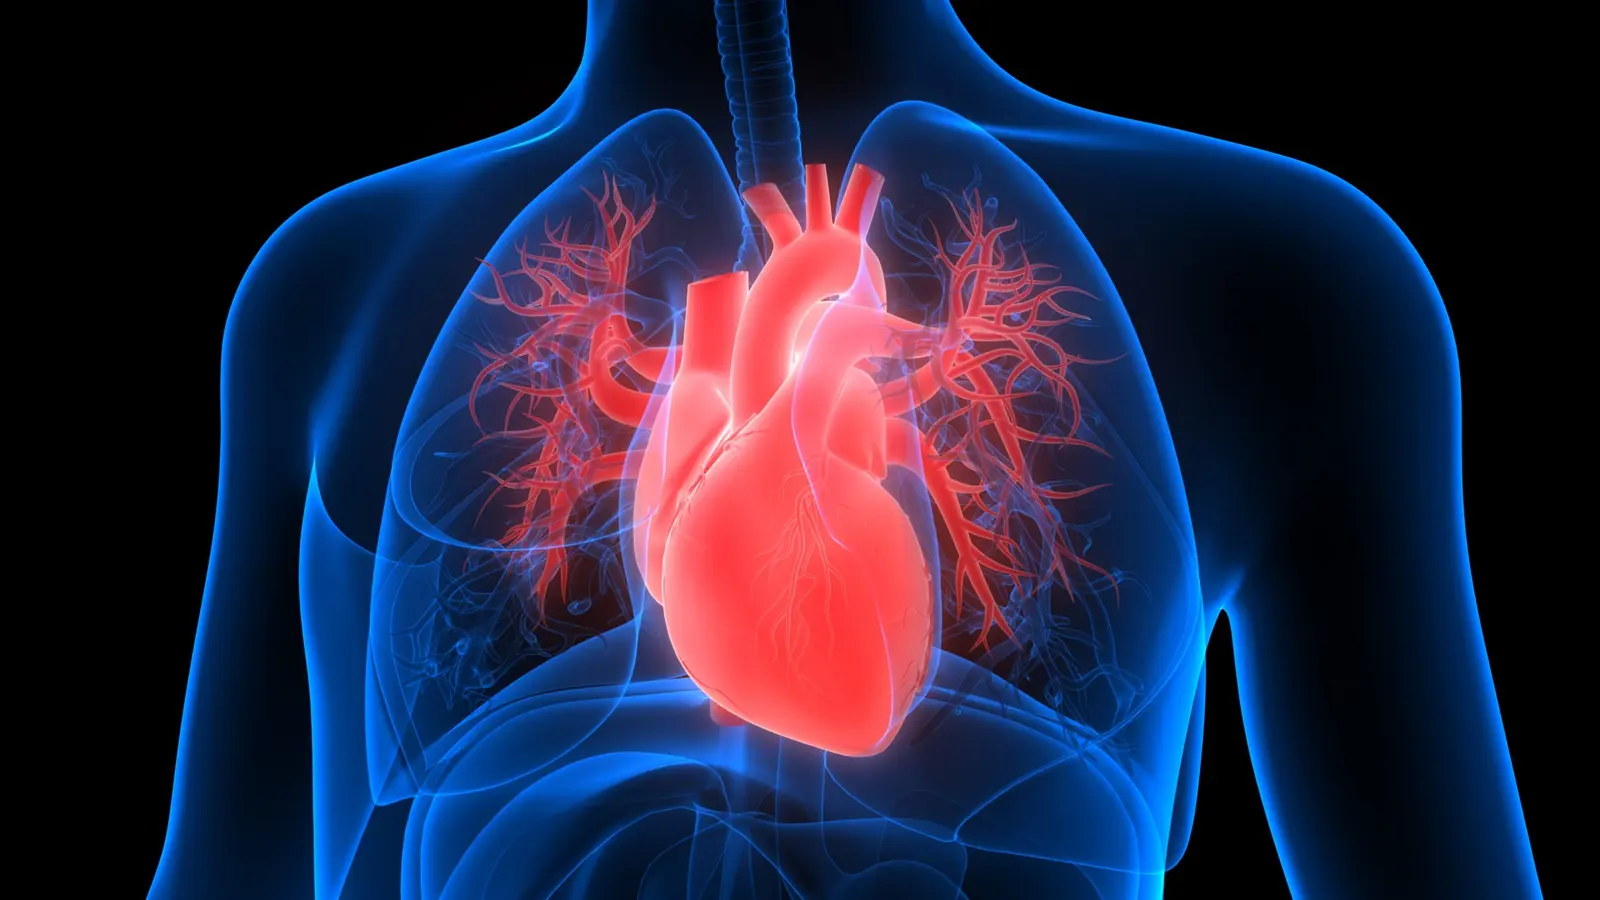
B-type natriuretic peptide, or BNP, has long been a clinical alarm bell. Doctors measure it to spot heart failure early. But what if that alarm is not just a warning light? What if it nudges the body toward a secondary danger: unwanted blood clots?
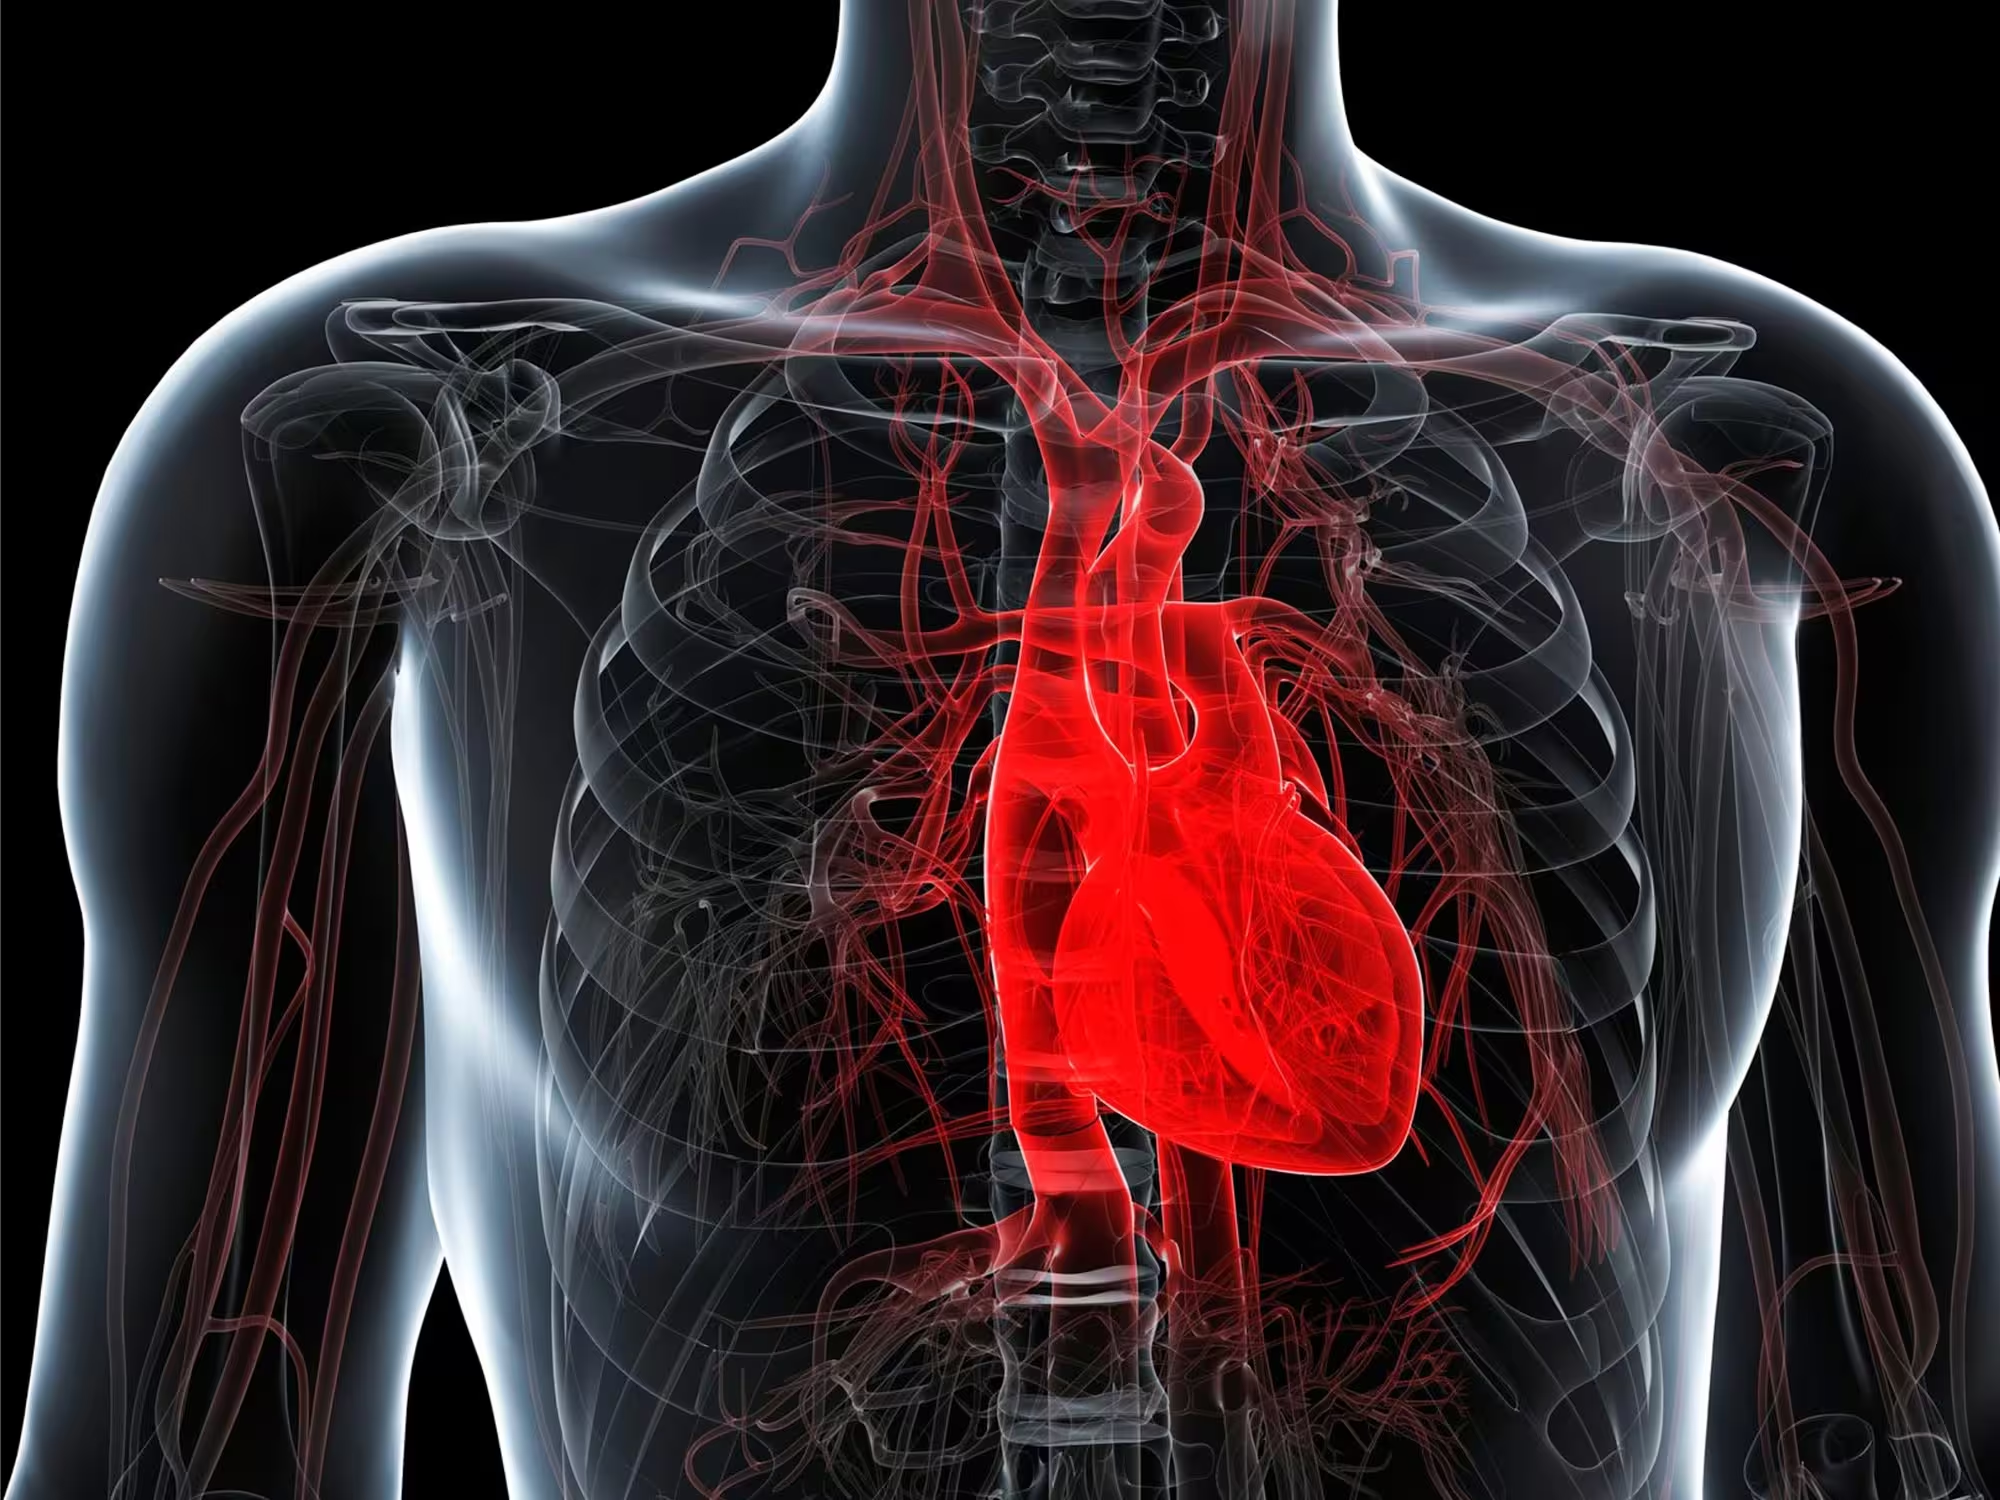
B-type natriuretic peptide (BNP) is a hormone released by the heart in response to increased pressure and strain. It helps regulate blood pressure and fluid balance by promoting the removal of excess sodium and water. Elevated BNP levels are commonly used as a warning sign of heart failure and other cardiovascular problems.
A common blood alarm that backfires
It sounds counterintuitive. A molecule we use to detect failing hearts appears to play an active role in a separate, lethal process. Yet recent laboratory work from Texas A&M researchers shows BNP directly stimulates platelets, the tiny cells that glue wounds closed. When platelets become overactive, clots form inside intact vessels. Those clots can choke blood flow to the heart, lungs, brain, and other organs.
Platelets are heroes in the right place and time. They seal breaks and stop bleeding. But they are also the culprits behind heart attacks and pulmonary embolisms when they aggregate where they should not. The new data track BNP’s effect to a specific surface receptor on platelets, natriuretic peptide receptor-A, abbreviated NPRA. BNP binds NPRA and sets off an intracellular cascade that increases levels of cyclic guanosine monophosphate, or cGMP. That signaling shift makes platelets stickier and speeds up clot formation.
In controlled experiments that simulated blood-vessel injury and pulmonary embolism, higher BNP levels produced faster and larger clot growth. The effect was not subtle. When researchers blocked NPRA or genetically removed the receptor, BNP lost its power to raise cGMP and failed to provoke platelet activation. In those models the animals were protected from abnormal clotting.
Inside the platelet: NPRA and cGMP
How can a hormone associated with fluid balance affect clotting? The answer lies in cell signaling. Receptors like NPRA translate external chemical messages into internal actions. In many tissues BNP binding to NPRA increases cGMP, a messenger molecule that drives particular enzymatic changes. On platelets, this rise in cGMP appears to lower the threshold for activation, so platelets respond more readily to cues that normally trigger clotting.
That pathway explains a curious clinical observation. Patients with elevated BNP often face higher rates of thrombotic events. Until now, clinicians treated BNP as an indicator of cardiac stress; the peptide itself was not suspected of promoting thrombosis. The Texas A&M team’s experiments provide a plausible mechanistic link between high BNP and thrombosis risk.
Blood samples from people with abnormal heart rhythms added human context. Individuals with higher circulating BNP showed greater platelet activity, consistent with the lab findings. Correlation is not causation, of course. But the concordance between patient data and mechanistic experiments strengthens the hypothesis that BNP has a direct, actionable effect on clotting biology.
Therapeutic avenues and uncertainties
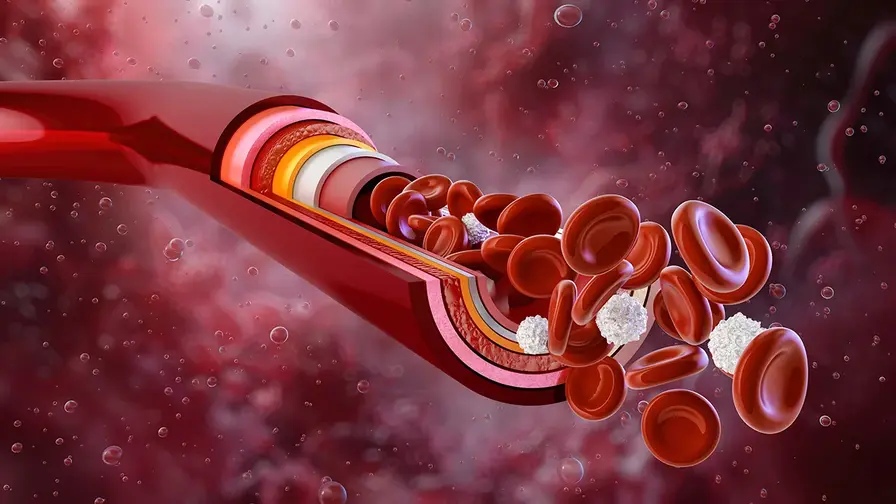
Current antiplatelet drugs blunt platelet function systemically. They reduce clot risk but raise the chance of dangerous bleeding. A more surgical solution would be to block BNP’s interaction with NPRA on platelets, preventing pathological clot formation while preserving normal hemostasis at wound sites.
Researchers are pursuing that idea. The team has begun screening small molecules that interrupt BNP-NPRA binding. Early-stage compounds will next be tested for their ability to stop BNP-driven platelet activation without impairing healthy clot formation. If successful, such agents could offer targeted protection for patients who show high BNP but cannot tolerate broad antiplatelet therapy.
Several questions remain open. For one, platelets are not the only cells that express NPRA. Endothelial cells, kidney cells, and others respond to BNP. Disentangling how much clotting risk stems from platelet NPRA versus receptor activity on other cells will require tissue-specific genetic models. Researchers plan to remove NPRA selectively from platelets and from other cell types to map each contribution precisely.
Timing matters as well. BNP levels can spike during acute heart failure episodes, after surgery, or during severe infections. When is an intervention most effective? Which patients would benefit most from a targeted NPRA blocker? Clinical trials, if and when they arrive, will need careful patient selection and safety monitoring to guard against unforeseen bleeding or interference with blood pressure regulation.
Why this matters for patients
The practical implication is immediate. Clinicians already use BNP to triage patients. The new findings suggest patients with persistent BNP elevation may warrant closer surveillance for thrombotic complications. It also gives physicians a biological rationale for considering antiplatelet strategies in certain high-risk patients, weighed against bleeding risk.
Long term, a therapy that stops maladaptive BNP signaling at NPRA could shift the balance: reduce thrombotic events without the price of widespread anticoagulation. That would be particularly valuable for people with chronic heart failure, atrial arrhythmias, or other conditions where BNP remains chronically raised.
Expert Insight
"This work reframes how we think about biomarkers," said Dr. Elena Morales, a cardiovascular researcher and clinician not involved in the study. "BNP has been an early warning system for decades. Now it appears to be part of the emergency itself. The goal is to intervene precisely where BNP crosses from signal to driver, so we preserve the peptide’s beneficial roles while removing the harmful ones."
Dr. Zhenyu Li, who led the Texas A&M study, described the progress as cumulative rather than sudden. "It was not a single eureka moment," he said. "This finding builds on years of work dissecting platelet biology and its links to cardiovascular disease." He added that collaboration with chemists to identify NPRA blockers is already underway.
Conclusion
BNP is more than a passive indicator of heart strain. Evidence now shows it can engage platelet receptors and accelerate clot formation in experimental systems. That discovery reframes a familiar clinical test as a potential therapeutic target. The path forward includes validating the mechanism in humans, developing selective NPRA inhibitors, and designing trials to test whether targeted blockade can reduce thrombotic events without increasing bleeding. Until then, elevated BNP should prompt careful clinical vigilance and a nuanced discussion about clot risk and prevention strategies.

“The cosmos has always fascinated me. I write about space missions, astronomy, and the technologies pushing humanity beyond Earth.”

Discussion
Leave a Comment
Comments
No comments yet. Be the first.