
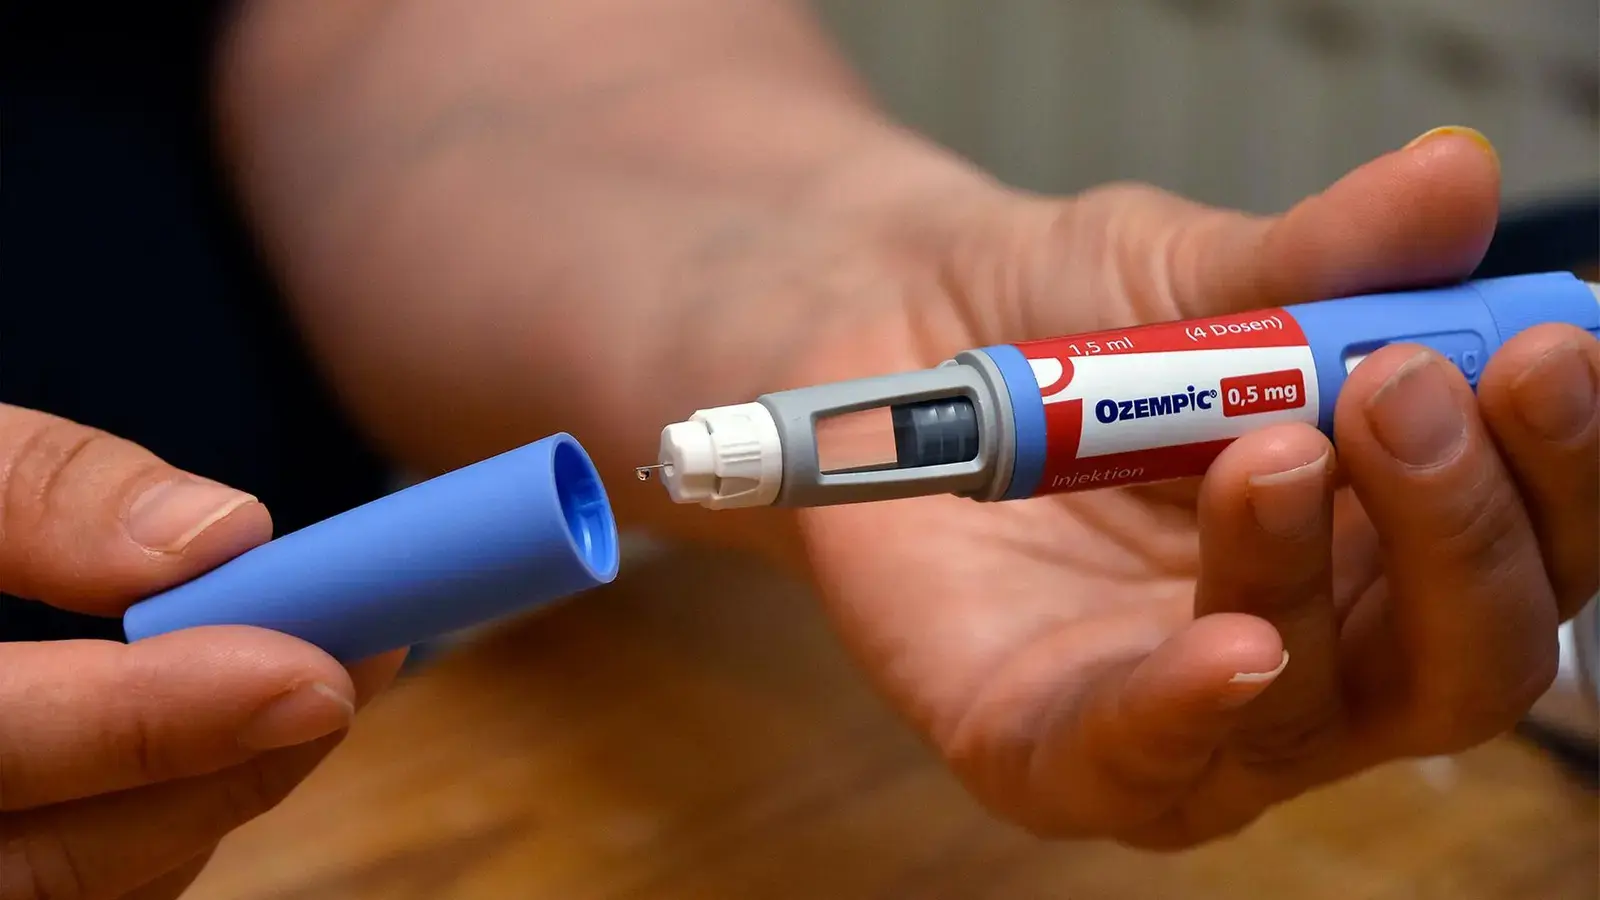
People describe dramatic transformations after starting GLP-1 medications like Ozempic. Clothes fit differently. Energy shifts. Social routines change. But when researchers looked for broad, measurable shifts in everyday life, the picture was quieter than the headlines suggested.
Ozempic and similar drugs deliver clear medical benefits, but their broader effects may be less obvious. New research found little measurable change in mental health, work, or marriage. Credit: Shutterstock
A working paper from the National Bureau of Economic Research, led by University of Chicago economist Robert Kaestner and coauthor Cuiping Schiman, probed whether the known clinical wins from GLP-1 agonists translate into detectable gains across mental well being, employment, and marital status for adults with diabetes.
Following people, not groups
The strength of this study lies in its design. Instead of the usual side-by-side comparison of users versus nonusers, the researchers tracked the same individuals over time. That method reduces the misleading signals that can arise when early adopters differ from the rest of the population in ways that have nothing to do with the drug itself.

They used more than a decade of data from the Medical Expenditure Panel Survey, covering adults with diabetes between 2012 and 2023. The team examined standard indicators: symptoms of depression, psychological distress, self rated health, employment status, and whether people married or divorced after initiating GLP-1 treatment.
At first glance, simple cross sectional comparisons suggested differences. GLP-1 users appeared more likely to be employed and married. Those initial gaps looked promising. But when each person served as their own control and outcomes before and after treatment were compared, most of those apparent changes evaporated.
Whether the researchers looked one year after starting or extended the follow up to two years, the results were consistent. There was little evidence that beginning GLP-1 therapy produced meaningful shifts in the broad social and economic measures under study.
That is not the same as saying nothing changed at all. Instead, the evidence implies that the headline effects—better blood sugar control, weight loss, fewer cardiovascular risks—were not accompanied by large, measurable moves in marriage rates, employment, or conventional mental health scales during the windows observed.
Why standard measures might miss the point

Kaestner cautioned that absence of proof is not proof of absence. Standard population metrics capture clear, categorical outcomes. They do not always reflect subtle shifts in confidence, daily functioning, or relationship quality.
Imagine two people who both keep their jobs after treatment. One returns to the same role with renewed energy and fewer sick days. The other barely notices any change. A dataset that records employment as a binary status will label both outcomes the same way. Likewise, marital status does not measure intimacy, conflict, or improvements in partnership dynamics.
“We know these drugs improve health outcomes, and there’s been a great deal of research documenting those benefits,” Kaestner said. “What hadn’t really been examined was whether those improvements extended into other parts of people’s lives—things like employment, relationships, marriage, and mental health.”
The study therefore leaves open the possibility that meaningful but nuanced benefits exist. These could be person specific. They could emerge more clearly over longer time spans. Or they could show up most strongly in populations using GLP-1 medications primarily for weight management rather than diabetes control.
From a policy standpoint, that distinction matters. Insurers and public programs weigh not only clinical effectiveness but also broader social and economic returns when considering coverage expansions. Solid evidence of downstream gains in employment or mental health would strengthen the case for wider access. The current results, however, suggest such social returns are not yet obvious in standard national surveys.
Expert Insight
Dr. Elaine Park, a health economist not involved in the paper, offers perspective: “These medications are an extraordinary clinical tool. Expecting them to produce large shifts in marriage or employment within a couple of years may be unrealistic. Social outcomes are influenced by many forces. To detect secondary effects we need targeted measures that capture changes in daily functioning, social participation, and self perception.”
She recommends future work that combines qualitative interviews with administrative data, and studies that follow people for longer periods after starting treatment. That mixed approach would be better suited to reveal slow moving or subtle changes that standard questionnaires miss.
The medical case for GLP-1 therapy remains strong. Clinical trials and observational studies reliably show benefits for glycemic control, weight reduction, and some cardiovascular outcomes. What Kaestner and Schiman add is an early, careful look at whether those benefits ripple into broader life domains. For now, the ripples are small or hard to detect with typical population measures.
Researchers will likely return to this question as GLP-1 use expands beyond diabetes into obesity treatment and into different age groups. Longer follow up, richer social measures, and studies tailored to people seeking weight loss could reveal patterns that national surveys cannot.
In short, GLP-1 drugs change bodies in demonstrable ways. Whether they change lives at scale remains an open question that deserves more nuanced, longitudinal study.

“The cosmos has always fascinated me. I write about space missions, astronomy, and the technologies pushing humanity beyond Earth.”

Discussion
Leave a Comment
Comments
No comments yet. Be the first.